Partially Hydrolyzed Guar Gum for IBS: A Gentler Fiber, Not a Guaranteed Fix
A practical guide to PHGG for IBS, including what trials measured, how it differs from intact guar gum, and how to start cautiously.

PHGG is a soluble fiber with some IBS-specific trial evidence, especially for bloating, but dose, tolerance and the rest of the diet still matter.
Why PHGG can feel different from ordinary guar gum
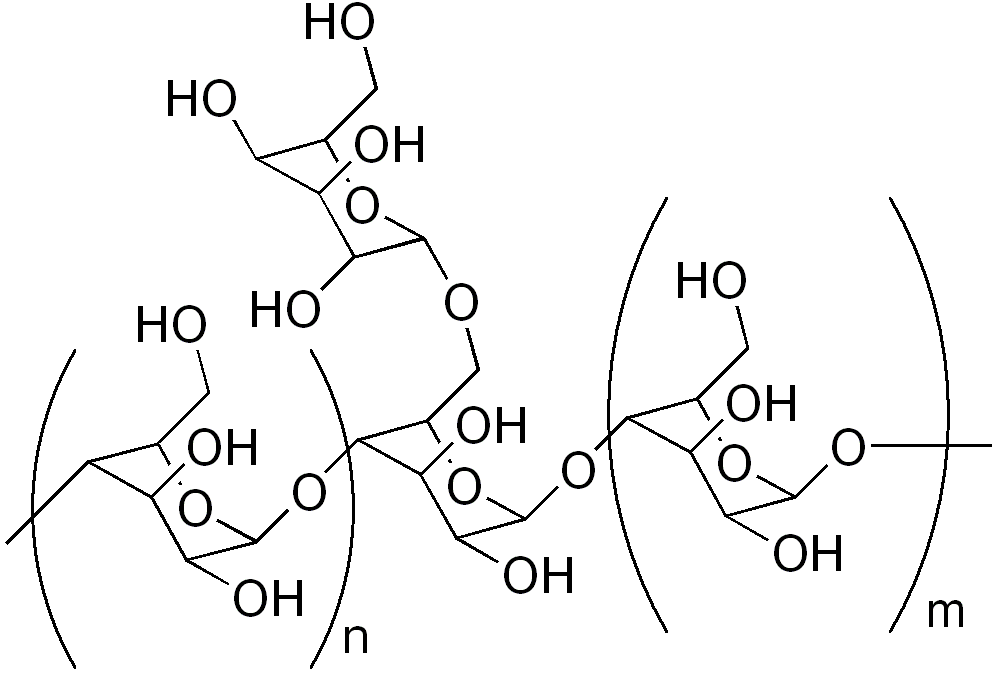
A fiber that supports bowel regularity without turning every meal into a gas experiment sounds appealing. Partially hydrolyzed guar gum, usually shortened to PHGG, is made by breaking long guar-gum chains into smaller pieces. It remains a soluble, fermentable fiber, but it dissolves easily and is far less thick than the intact gum used to thicken foods.
That distinction matters if you are comparing soluble and insoluble fiber for IBS. Soluble fibers interact with water and gut microbes, while coarse insoluble fibers can feel abrasive or increase urgency for some people. PHGG is not the same product as culinary guar gum, and results from one should not be casually assigned to the other.
What the IBS trials actually found
In a double-blind randomized trial, adults with IBS who took 6 grams of PHGG daily for 12 weeks reported a greater improvement in bloating than the placebo group. The trial did not show that every IBS symptom disappeared, and it did not establish PHGG as a cure. It offers a focused signal for one symptom that often drives discomfort.
Earlier randomized work compared PHGG with wheat bran and also tested PHGG against an unrestricted diet. Those studies generally found acceptable tolerance and symptom improvement, but their designs, doses and endpoints differed. The evidence is useful, not uniform. It also explains why a personal response may differ from the average result in a research group.
Gas, dose and the microbiome
Because colonic bacteria can ferment PHGG, some gas is biologically plausible, especially after a sudden dose increase. That is also why an inulin bloating and dose-tolerance guide can be useful context: two fermentable fibers can behave very differently in the same person. A label saying prebiotic does not predict comfort, and more grams do not automatically mean more benefit.
PHGG fermentation can change microbial activity and short-chain fatty-acid production, but those laboratory or stool changes are not a direct promise of symptom relief. Clinical outcomes matter more than a microbiome buzzword. Keep a simple note of dose, stool pattern, bloating and pain rather than chasing a particular bacterial profile.

How to try it without rushing
Start below the full label dose if your clinician agrees, then increase gradually over several days. Mix it into enough fluid and keep total fluid intake steady. If constipation is the main problem, compare that plan with a psyllium water and medication-timing guide, since psyllium gels differently and has a broader constipation evidence base.
Change one fiber at a time. Adding PHGG while also doubling beans, starting a probiotic and removing several FODMAP groups makes the result impossible to read. Separate supplements from medicines by the interval your pharmacist recommends, because added fiber can affect how quickly some oral products move through the gut.
A practical decision point
PHGG may be worth discussing when IBS bloating or irregular stools persist and a low-thickness soluble fiber seems easier to use. Acacia fiber trials in IBS and constipation provide another option to compare, but products are not interchangeable gram for gram. Choose one approach, use a measured amount and give symptoms time to settle.
Stop and seek medical advice for bleeding, unexplained weight loss, fever, persistent vomiting, anemia or a major new change in bowel habits. Those signs deserve evaluation, not a longer supplement experiment. For ordinary IBS management, a slow, documented trial gives you far more useful information than an aggressive dose on day one.
When comparing products, choose one that states PHGG clearly and gives grams per serving. A generic fiber blend may contain other fermentable ingredients that change tolerance. Check flavoring, sweeteners and serving instructions too. The most useful experiment has a known ingredient, a repeatable dose and a defined goal such as less bloating or easier stool passage.
A simple stop rule helps too: if bloating keeps rising after a careful dose reduction, the fiber may not suit your current IBS pattern.